

The average Medicare Advantage supplemental premium in 2026 sits at just $14.00 a month, and roughly 60% of plans charge $0 on top of your Part B premium. But the number that actually determines your worst-case year is the out-of-pocket maximum, which averages $5,421 in-network and $9,825 combined this year. Part D drug costs are tracked on a completely separate cap, so your premium alone tells you almost nothing about what you’d owe in a bad year.
TL;DR:
- Most Medicare Advantage plans in 2026 will have premiums around $14 monthly, with 60% charging nothing beyond the Part B premium.
- Copays, coinsurance, and deductibles count toward your MOOP, but premiums and Part D drug costs do not.
- Plan type significantly affects costs, with HMOs averaging lower MOOPs than PPOs, but restricting you to in-network providers.
- Always compare plan benefits against your prescriptions, doctors, and ZIP code during open enrollment to avoid hidden costs and plan changes.
Table of Contents
- What Are Medicare Advantage Costs in 2026?
- What Do You Actually Pay in a Medicare Advantage Plan?
- Does HMO or PPO Change What You Pay?
- How Do You Estimate Your Annual Medicare Advantage Cost?
- Where Do Medicare Advantage Costs Go Wrong?
- How Safeguard Benefit Services Helps You Read the Numbers
- Get a Personalized Medicare Advantage Cost Estimate
- Sources
What Are Medicare Advantage Costs in 2026?
Here’s the quick reference most people are searching for, straight from the federal data:
- Average MA supplemental premium: $14.00 a month, with close to 60% of plans charging $0 beyond Part B.
- Part B standard premium: $202.90 a month for most enrollees, paid regardless of which MA plan you pick.
- Average out-of-pocket maximum (MOOP): $5,421 in-network, $9,825 combined in-network and out-of-network.
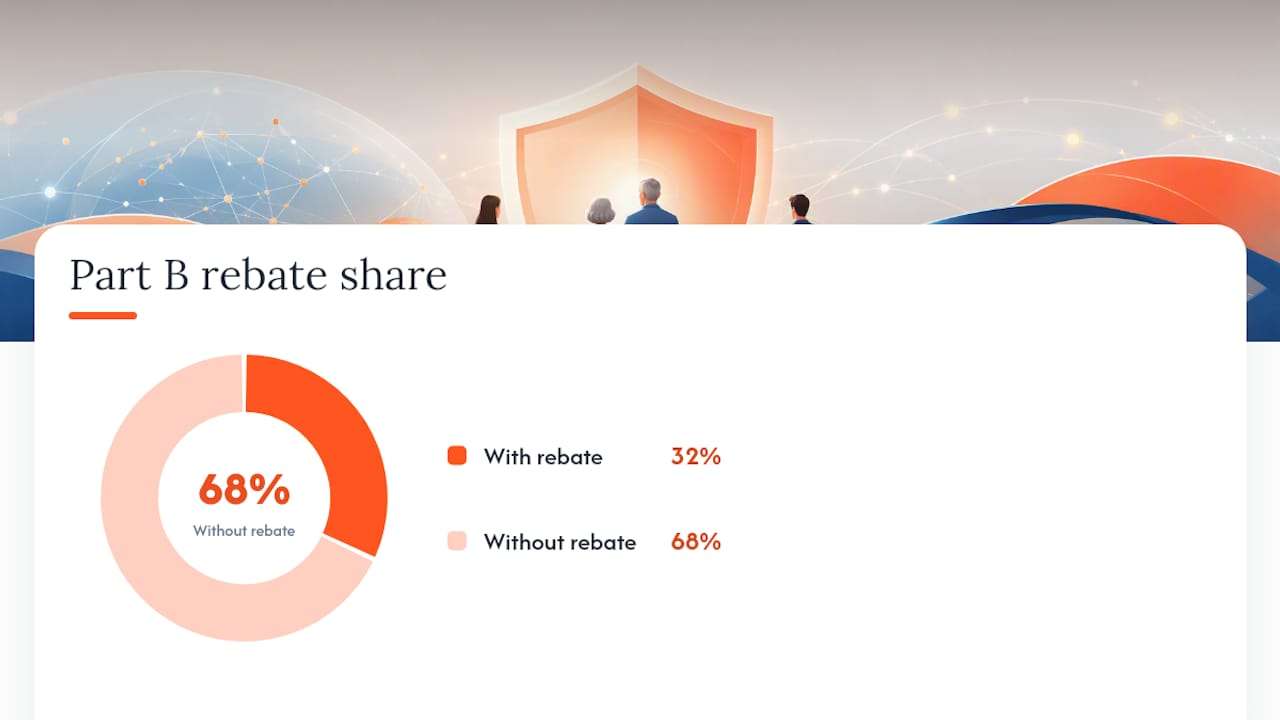
- Part B rebates: About 32% of individual plans use rebate dollars to lower your Part B premium.
- Part D: Tracked and capped separately from your medical MOOP. See our 2026 Medicare cost breakdown for how the pieces interact.
Pro Tip: Bookmark the CMS 2026 announcement and check it against your plan’s Annual Notice of Change letter every fall. The national averages rarely match what a specific plan in your county charges.
What Do You Actually Pay in a Medicare Advantage Plan?
Four terms drive your bill, and confusing them is the most common mistake we see. A premium is what you pay monthly just to stay enrolled. In Medicare Advantage, that’s your plan’s supplemental premium plus the Part B premium, which every Medicare enrollee pays no matter which plan they choose. Even a $0 MA plan still comes with that Part B charge attached.
A deductible is what you pay out of pocket before your plan starts sharing costs on certain services, often drugs or specific medical categories rather than one blanket amount. A copay is a flat fee, say $20 for a primary care visit or $45 for a specialist. Coinsurance is a percentage, commonly 20% of the cost for outpatient procedures or durable medical equipment.
Here’s what matters most: copays, coinsurance, and your medical deductible all count toward your MOOP. Your monthly premiums don’t count toward it, and neither does your Part D drug spending, which runs on its own separate cap explained further down.
- Premium: monthly cost to stay enrolled (plan premium + Part B).
- Deductible: what you pay before cost-sharing kicks in on covered services.
- Copay: fixed dollar amount per visit or service.
- Coinsurance: percentage of the cost you owe after any deductible.
For plan-specific numbers, always pull the Summary of Benefits and Evidence of Coverage documents directly, or read our primer on premiums, deductibles, and out-of-pocket costs for a fuller walkthrough.
Does HMO or PPO Change What You Pay?
Plan type changes your cost structure more than almost any other single choice. HMOs average $4,636 in-network MOOP, while PPOs average $6,592, according to KFF’s 2026 analysis. That gap exists because HMOs concentrate enrollees into tighter networks, which gives insurers more negotiating leverage and lets them keep both premiums and caps lower.
PPOs charge you more for that flexibility, but they let you see out-of-network specialists without a referral, a real advantage if you split time between two states or have a specialist outside your local network. Some plans offset their premiums using CMS rebate dollars, either by lowering your Part B premium directly or by funding dental, vision, and hearing add-ons.
- HMOs: lower premiums and MOOPs, but you’re locked into an in-network primary care doctor and referrals.
- PPOs: higher MOOPs on average, but you keep out-of-network access.
- Part B rebates: available on about 32% of plans, either as a premium cut or extra benefits.
Our HMO vs. PPO guide for Charlotte residents breaks down which local networks tend to favor each type.
Pro Tip: If you see three or more specialists regularly or travel part of the year, a higher-premium PPO often costs less overall than an HMO once you factor in avoided out-of-network penalties.
How Do You Estimate Your Annual Medicare Advantage Cost?
Before opening Medicare, gather this list:
- Every doctor and specialist you see, with names and locations.
- Current prescriptions, exact dosages, and your preferred pharmacy.
- Any procedures or treatments you expect this year (surgery, physical therapy, imaging).
- Your rough number of office visits per year.
- Your ZIP code, since plan pricing and networks vary by county.
Enter your drugs and pharmacy into Plan Compare first. It will show your estimated annual drug cost per plan before you even look at medical premiums. Then add the Part B premium, your plan’s supplemental premium (minus any rebate), and estimate two scenarios: a typical year and a high-use year capped at your plan’s MOOP.
| Scenario | Monthly premium | Estimated typical-year cost | Worst-case cap (MOOP) |
|---|---|---|---|
| Low-use retiree, HMO | $0 supplemental + $202.90 Part B | $14.00 a month | $4,636 in-network |
| Chronic condition, PPO | $35 supplemental + $202.90 Part B | $6,592 | $9,825 combined |
These are illustrative ranges based on national averages, not guaranteed figures for any specific plan. Your actual numbers depend entirely on your ZIP code, drug list, and plan selection.
Where Do Medicare Advantage Costs Go Wrong?
A $0 premium plan can still cost you more over a full year than a plan charging $35 a month. Higher copays, tighter networks, and more prior authorization requirements often hide behind that attractive $0 headline, and a couple of urgent care visits or a hospital stay can erase the premium savings fast.
Remember that Part D spending doesn’t count toward your medical MOOP. If you’re managing several prescriptions, check the Part D coverage guide separately, since manufacturer coupons typically don’t count toward your drug out-of-pocket threshold either. For general strategies on managing prescription spending, the GLPCare guide on lowering drug costs covers tactics that apply beyond Medicare too.
- Watch for narrow provider directories that exclude your current doctors.
- Check whether your medications appear on the formulary at your current tier.
- Count the number of services requiring prior authorization.
- Re-verify everything during Fall Open Enrollment, since plans change benefits every year.
Pro Tip: Never assume last year’s coverage carries over unchanged. Insurers routinely adjust formularies, networks, and cost-sharing between plan years.
How Safeguard Benefit Services Helps You Read the Numbers
We walk clients through the same math outlined above: comparing plans, checking formularies against actual prescriptions, and flagging enrollment deadlines that carry lifetime penalties if missed. Every client gets a free, personalized Medicare roadmap that turns CMS averages into numbers specific to their ZIP code and health needs. Our agents complete ongoing training specifically so they can catch the network and formulary gaps that make a cheap-looking plan expensive in practice.
— Zach
Get a Personalized Medicare Advantage Cost Estimate
Averages tell you what’s typical. They don’t tell you what your specific doctors, prescriptions, and ZIP code will actually cost under a real plan. Some agencies close the gap for Medicare-eligible residents by offering free, one-on-one consultations that run your actual drug list and providers through the numbers instead of leaving you to guess from national averages.
During a consult, we compare plan options side by side, check your medications against each plan’s formulary, and confirm your enrollment timing so you avoid late penalties. If you want the full picture on how Medicare Advantage plans work before you talk to anyone, start with our Medicare Advantage Plans Explained guide. If you’re local, the Charlotte-area Medicare Advantage page has details on in-person appointments, and assistance may also be offered remotely by phone across North Carolina. Call or request a Medicare roadmap today to get numbers built around your actual coverage needs, not just the national average.
This article is general information, not a substitute for advice from a qualified financial advisor. Consult a qualified financial professional about your own circumstances before acting on anything here.
Sources
- Medicare Advantage and Medicare Prescription Drug Programs Expected to Remain Stable in 2026 | CMS
- Medicare Advantage in 2026: Premiums, out-of-pocket limits, supplemental benefits, and prior authorization | KFF
- Medicare Advantage Plan Cost 2026 | MoneyGeek
- Medicare
Recommended
- Medicare Costs: Premiums, Deductibles And Out-of-Pocket Expenses In 2026
- Understanding Medicare Costs: Premiums, Deductibles, And Out-of-Pocket Expenses
- Medicare Advantage Vs Medicare Supplement: Which Plan Fits You?
- Medicare Advantage Plan Vs. Medicare Supplement Plans: Choosing The Best Option For You In 2025
Request a No Obligation Phone Call








Get Connected